

25 Baiga Children Have Died in Madhya Pradesh. Inequality, Not Tribal Customs, is at the Heart of It


A recent measles-rubella outbreak in the Birsa-Baihar region of Balaghat district, Madhya Pradesh, has drawn attention to the precarious health conditions of the Baiga people – one of India’s forest-based indigenous communities. At least 25 Baiga children have reportedly died in Bondari, Kondekasa, Macchurda, Gatiya, Matla and other villages, while many others are fighting the illness. Local reports suggest that cases of the outbreak had been appearing since January. However, it was only after the sarpanch of Adori village informed the sub-divisional magistrate about a death on July 22 that a substantial administrative response followed.
Health officials have identified several possible causes of the deaths, including measles, Plasmodium falciparum malaria, and E. coli contamination of water. The coexistence of these conditions makes it difficult to attribute it to a single pathogen. A medical anthropological perspective, therefore, requires a broader question: beyond what caused these deaths biologically, why did the infections become so deadly only among Baiga children?
The Baiga community is classified as a Particularly Vulnerable tribal group (PVTG) due to their historical, socioeconomic and demographic conditions. The Dhebar Commission had associated such communities with pre-agricultural subsistence practices, including hunting and gathering, very low literacy and stagnant or declining populations.

Baiga children undergoing treatment for the measles-rubella outbreak, in Madhya Pradesh. Photo: Jay Ramteke
However, describing the Baiga as inherently “vulnerable” risks obscuring how vulnerability is produced through contemporary political, economic and institutional arrangements. During the field visits, residents complained that they have not received supplementary nutrition for nearly six months. The nearest hospital in these villages is nearly 20 kilometres away, and they also alleged that they are often reprimanded by the forest department when they try to access the forests. These conditions restrict their access to basic resources, turning social and institutional inequalities into biological vulnerability.
Thus, the Measles-Rubella outbreak in Balaghat district demonstrates that vulnerability is not simply a characteristic of a community. It is also a condition imposed upon them by the state.
When disease has more than one explanation
In the affected villages, biomedical and indigenous explanations of illness coexist. When I visited these villages, health officials on-duty in Kondekasa village described the outbreak as an infectious disease such as measles, contaminated water or malaria, Baiga residents offer a different explanatory framework.
Measles is locally known as ‘chhoti mata’. The villagers described it as a familiar childhood illness that has occurred among previous generations. However, what appears different in the current outbreak is its severity, causing a larger number of deaths. Some community members have interpreted it spiritually, suggesting that the deities associated with the illnesses have become angrier this time – an occurrence they called “Daaban”, which happens once in a decade.
In Bondari village, residents offered another explanation: older gunias, or ritual specialists, have died, while younger gunias are believed to lack the knowledge required to perform effective rituals.
These explanations should not simply be dismissed as superstitions. Medical anthropology recognises that communities develop explanatory models through which they understand illness, suffering and recovery. These models also influence decisions about when and where to seek treatment.
Importantly, the existence of an indigenous explanation does not necessarily mean that biomedical healthcare is rejected. Families may move between healers, household remedies, community health workers and government hospitals. This movement between different therapeutic systems is what constitutes medical pluralism.
The problem, however, emerges when one system is treated as legitimate and the other as an obstacle.
Food, land and vulnerable bodies
Baiga people also linked the severity of the current outbreak to changes in dietary practices. Speaking to The Wire, community members like Deva Baiga, who is the co-founder of Baiga tribal society for development, pointed to the declining consumption of traditional millets such as kodo and kutki, arguing that earlier generations were physically stronger because these foods were an important part of their diet. This highlights an important relationship among food, ecology and health.
Nutrition is not only a question of whether food contains sufficient calories or micronutrients. It is also determined by access to land, forests, agricultural resources and markets.
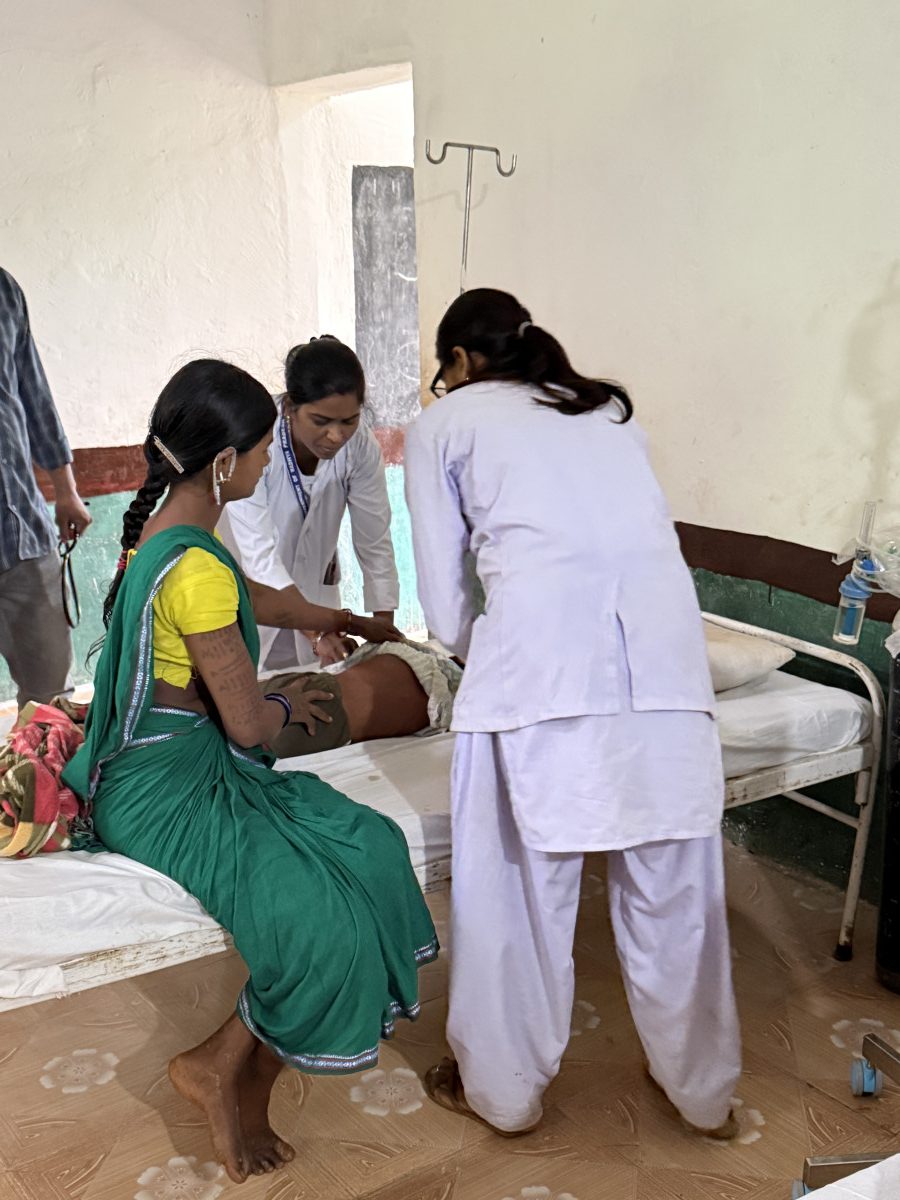
Baiga children undergoing treatment for the measles-rubella outbreak, in Madhya Pradesh. Photo: Jay Ramteke
Changes in cultivation practices, restrictions affecting forest-based livelihoods and the increasing role of market intermediaries can transform what communities grow and eat. Traditional foods have also increasingly become commodities for sale rather than being retained for household consumption.
A child’s vulnerability to an infection is, thus, also linked to such processes. Changes in land use, food systems and livelihood practices have eventually become biological vulnerabilities.
Vaccine hesitancy and the question of trust
Most of the frontline health workers working in the villages cited low vaccination coverage as a major reason behind how the infection has spread. “These people do not get their children vaccinated. Whenever we visit the villages for a vaccination drive, they either go to the jungles or go out for work. Sometimes they take children to the nearest panda (priest),” said one health worker.
According to them, the Baiga people’s hesitancy towards vaccines is the main reason behind this outbreak. Yet, describing the problem simply as “vaccine hesitancy” risks reducing a complex social relationship to a problem of ignorance.
Baiga community members have expressed concerns about vaccines, including the permanent BCG scar on the left arm. The scar is perceived as an externally imposed mark, something that permanently inscribes itself onto the body. Some Baiga people also perceive vaccination as the introduction of an alien substance that could weaken the body.
These concerns must be understood within the broader relationship of Baiga communities with state institutions. Healthcare trust is built through everyday encounters, and not just during emergencies. If medical personnel appear primarily during outbreaks, and when healthcare facilities are distant; when communication is difficult or when indigenous healing practices are dismissed and taken as superstitions, distrust deepens. Vaccine rejections or acceptance is therefore not merely an informational problem. It is also a question of institutional trust.
Geography of healthcare and the making of vulnerability
Geography further shapes this vulnerability. The Birsa-Baihar region of Madhya Pradesh is largely made of forested areas. For the villages in the region, transportation and access to higher-level healthcare is difficult. Community members and healthcare workers, too, pointed to the challenges of maintaining regular medical services in these locations. Physical distance is only one dimension of healthcare accessibility; language and cultural distance matter as well.

The villages where the Baiga people largely reside fall under the Birsa-Baihar region of Madhya Pradesh, which is largely made of forested areas making healthcare and basic amenities distant and difficult to reach. Photo: Jay Ramteke
Dulesh Baiga, also a co-founder of Baiga tribal society for development, explained this to The Wire. “In hospitals, the major problem that our community members face is the language. The way we describe any illness is different; doctors and nurses sometimes laugh at our vocabularies, misinterpret how we define things and then blame us. A Baiga takes the body to the hospital but their mind or soul still stays in the forest,” he said.
Baiga patients frequently encounter such medical institutions where their ways of describing an illness are poorly understood. Communication determines whether symptoms are adequately explained, treatment instructions are understood, and patients feel respected. A hospital for Baigas, therefore is physically present but socially and culturally distant.
Moreover, the concept of structural violence also offers a useful way of understanding the outbreak. A child may die from measles, malaria, dehydration, or another infection, but the conditions determining whether that illness becomes fatal may have been produced over many years. When traditional food systems are weakened, access to forest resources is restricted, healthcare facilities are distant, doctors and medicines are unavailable, and when communication between communities and medical institutions remains poor, biological vulnerability is produced through social structures.
The PVTG category itself consequently becomes paradoxical: it recognises vulnerability, but recognition does not necessarily guarantee adequate protection. A population can be officially classified as vulnerable while continuing to experience inadequate nutrition, healthcare and infrastructure.
A structural neglect
The Balaghat measles-rubella outbreak, therefore, demonstrates that 'tribal vulnerability' is a product of structural neglect and exclusion, rather than a characteristic of the community.
The Baiga children are dying, but the question “why?” cannot be answered by naming a pathogen alone.
From a medical anthropological perspective, illness is never purely biological; it is experienced through histories of land, food, livelihood, belief, medicine and power. Measles or malaria may explain the immediate cause of death. Yet, the conditions that make the illness deadly are social: disrupted food systems, weakened access to traditional resources, distant and culturally unfamiliar healthcare, inadequate nutrition, and mistrust between communities and biomedical institutions.
The Baiga people’s explanations of ‘chhoti mata’, the role of traditional healers, traditional foods, and vaccine hesitancy reveal not ignorance but an alternative way of making sense of illness and the body.
The deaths show that vulnerability is not an inherent condition of the Baiga community – it has been produced through unequal relations between communities, institutions and their environments. To understand why the children are dying is consequently to examine not only the disease, but the social world in which that disease becomes fatal.
Jay Ramteke is a PhD student at the Department of Anthropology, Brandeis University, Boston, USA. He is also the co-founder of Paigam organization and Johar field school.
This article went live on August twenty-seventh, two thousand twenty six, at thirty-two minutes past three in the afternoon.The Wire is now on WhatsApp. Follow our channel for sharp analysis and opinions on the latest developments.


